

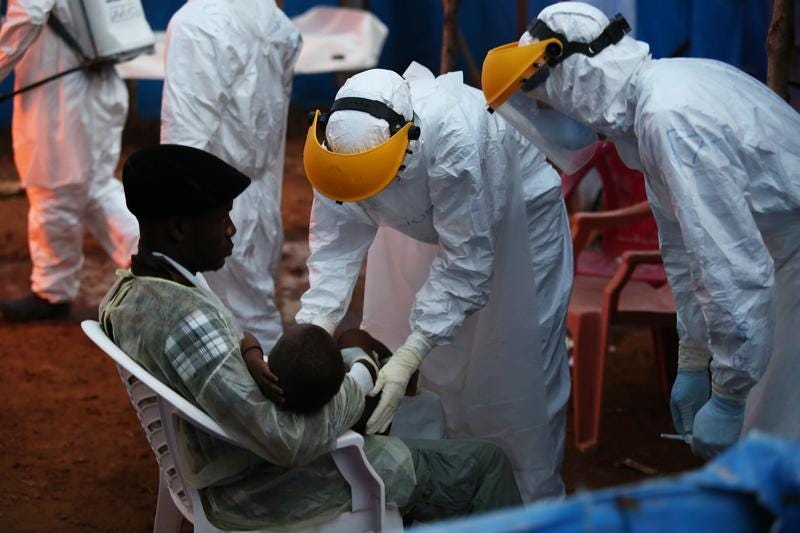
Bunia is the capital of the Democratic Republic of Congo’s Ituri region, near Lake Albert on the border with Uganda. This weekend people watched at a distance as health care workers in protective gear escorted the coffin of a of a six-month-old girl. She was one of three to die in an outbreak of the Bundibugyo strain of Ebola in an orphanage in the city. Over two hundred people have died among the approximately one thousand confirmed cases since the outbreak began in the DRC in mid-May of this year.
We can try to imagine these lives lost and the impact of these deaths on their families and communities, but it’s hard to comprehend something so distant. A person we don’t know dying in a far-off country from a virus we’re unlikely to ever see on our shores can be a tree falling in a forest to Canadians.
How can we understand what’s happening, let alone try to change it? We aren’t immediately affected and have nothing obvious to gain from intervening. Why should we help? Wouldn’t it be better to see international aid as a means of yes, improving life in other countries, but also using that aid to create economic opportunities for Canada?
That short-term thinking has infected the current discourse around overseas development assistance. The most notable example is the dismantling of USAID under Elon Musk and Donald Trump, but the focus on a narrow definition of mutual benefit has led many countries, including Canada, to reduce and restrict their efforts to improve life in the countries where people face the greatest hardships.
So what’s wrong with that? Why should we help others if it doesn’t help ourselves? The most obvious (and, sadly, most easily discarded) reason is the inherent value of human life. Valuing each person is a golden rule that goes beyond our immediate neighbours, beyond those who might someday return the favour, to understanding that we should wish the same health, happiness and opportunity for others that we wish for ourselves. PIH co-founder Paul Farmer famously said that “the idea that some lives matter less than others is the root of all that’s wrong with the world.” Conversely, a recognition of the deep importance of every human life comes the inspiration to do great things.
A world in which poverty is ignored unless its relief is of immediate tangible benefit to donor countries is one where death and disease reign unchecked in the places where suffering is greatest. It is a world of lost opportunity, a world of forced migration, instability and conflict. A world where we lift families out of poverty without asking what’s in it for us, will be a safer, healthier, more enjoyable place to live. Mutual benefit does exist, but, as Mark Brender, Executive Director of PIH Canada makes in today’s guest article, it requires a long-term perspective. That gradual but lasting return stems from the willingness to care about people’s lives as a gift, not a loan. Yes, generosity comes back to us, but the more we focus on cashing in on that return, the less effective we will be at creating a healthier future.
Mutual benefit in the context of Ebola
Every health emergency is an opportunity to see if we have learned lessons from the past. This is particularly true for the Bundibugyo strain of Ebola now surging in eastern Democratic Republic of Congo, where challenges to an effective response are immense.
No licenced vaccine exists for this strain and it’s difficult to diagnose, meaning the virus went unchecked for weeks before being identified. The outbreak is taking place in an area of longstanding conflict, limiting health worker access and contract tracing. It is difficult to know how many cases exist and how many deaths the outbreak has caused so far, but likely many months -- and more than $700 million, according to the World Health Organization -- will be needed to stop it.
Underlying it all is a health system stretched beyond its limits. The DRC spends about $33 per person a year on health, compared to government health spending of more than $6,900 per person in Canada. For the four billion people who lack access to quality care, weak health systems are at the root of so many challenges, including during disease outbreaks. And yet, almost in parallel, steep aid cuts from Western governments and the return of tied-aid frameworks last seen in the early 2000s – then explicitly rejected as counter-productive by recipient and donor countries alike, including Canada – have also been spreading.
Canada’s most recent federal budget made the most significant cuts to our international assistance commitments in a generation. The government has also stated Canadian aid should be leveraged to advance domestic economic interests, ensuring “mutual benefit” to Canadians and partner countries.
Details on what mutual benefit means and where it applies remain unclear but matter deeply. Global health spending represents less than one quarter of one percent of the federal budget and falling. This raises the urgency for remaining funds to be spent wisely. If Canadian economic benefit is applied to our global health aid, it will only deepen the consequences of global inequality the current Ebola outbreak is exposing. The greater the inequality, the more morally dubious our quest for mutual benefit becomes
Investing in health systems costs far less than epidemic response in lives and in dollars .
As experts have pointed out, Ebola carries a cruel irony in that it is a disease of caregivers. Because it moves from person to person through contact with bodily fluids, Ebola overwhelmingly infects and spreads through those who are showing compassion: family members providing comfort to sick relatives, nurses and doctors, people who prepare bodies for funerals.
Ebola is also a disease of inequality, thriving where health systems and immune systems are weakest. Diseases and health conditions don’t have fatality rates, health systems and social conditions do.
The West Africa Ebola epidemic of 2014-16 killed 11,000 people including 4,000 in Sierra Leone, where up to three out of every four people who contracted Ebola died. Eight of the nine Ebola-infected Western health professionals evacuated from Sierra Leone to Europe or the United States survived because they were able to access and receive the best supportive treatment when ordinary Sierra Leoneans could not.

For Ebola, as with all infectious diseases, prevention of transmission in times of crisis is linked with confidence and trust people feel for their health system. Once a crisis is underway, it’s too late to earn that trust. To be willing to follow public health protocols, people need to know from experience that their interactions with clinics, hospitals, and health professionals will make them and their loved ones well. Too often, in resource-poor settings, that’s not the case. Local communities know all too well that hastily assembled Ebola treatment units might be little more than containment centres designed only to prevent transmission rather than provide life-saving care.
Whether we place blame on legacies of colonialism, conflicts or unfair debt burdens and structural adjustment programs – or even on governments themselves – too many countries don’t have the fiscal space to invest appropriately in health. Ripples from these health system failures spread around the globe in lost trade, fractured relationships, and ill-advised border closures that make it harder to mobilize an effective response. It follows that strengthening weak health systems should be among our top aid objectives.
Investing in health systems costs far less than epidemic response in lives and in dollars – and we know how to do it. Partners In Health leverages the ‘5-S’ approach for health system strengthening: staff, stuff, space, systems, and social support. When we put them in place in partnership with local and national governments, we see better patient outcomes and stronger public sector capacity eventually leading to the country ownership and self-sufficiency everyone desires.

We also know what is ineffective: donor governments using aid as an opportunity to advance domestic agendas rather than contributing to country-led responses.
Responsive health systems and high citizen trust can and do exist in low-income countries. Rwanda ended a 2024 Marburg outbreak, equally dangerous to Ebola, in less than three months due to strong public health measures including activation of thousands of community health workers and a robust underlying health system designed to serve the most vulnerable.
In the aftermath of the 2010 Haiti earthquake and the failure of international assistance to advance Haiti’s long-term development, Paul Farmer outlined principles for improving aid effectiveness in what he called ‘acute on chronic’ contexts, when a crisis magnifies underlying health system weakness. Among his recommendations: The global community should localize aid dollars to create local jobs and boost local economies. Donors should allow ministries of health and other agencies to coordinate implementation in line with their needs and priorities. We also need to reassess how we see risk; we often overestimate risks to ourselves and underestimate “the risk of people living in poverty and dying needlessly.”
Finally, we need to make commitments that allow the transfer of aid functions to local authorities – what we now call ‘localization’ – to meaningfully take place. “This is not meant to be an excuse for aid agencies to leave before their local counterparts are strengthened,” Farmer wrote, “but rather a challenge for them to stay as long as it takes until these systems can stand on their own, and possibly even beyond, if needed.”
These are principles of the long-term mutual benefit of a safer and healthier world. The zeitgeist may be moving in the opposite direction, but disease outbreaks will end sooner and many more lives will be saved if we keep these ideas in mind rather than trying to extract transactional short-term gains that undermine the health of those most at risk.
Mark Brender is the National Director of PIH Canada.

Mark will be joining me in Saskatoon this Friday, June 26, at Hunger Cure Resto Bar from 7pm – 9pm. If you’d like to connect for informal conversation on Partners In Health, global health equity, our recent experiences in Rwanda and whatever else comes up, we’d love to see you there!